
Go to JCI Insight
  • About
  • Editors
  • Consulting Editors
  • For authors
  • Journal stats
  • Publication ethics
  • Publication alerts by email
  • Advertising
  • Job board
  • Contact
  • Clinical Research and Public Health
  • Current issue
  • Past issues
  • By specialty
    • COVID-19
    • Cardiology
    • Gastroenterology
    • Immunology
    • Metabolism
    • Nephrology
    • Neuroscience
    • Oncology
    • Pulmonology
    • Vascular biology
    • All ...
  • Videos
    • ASCI Milestone Awards
    • Video Abstracts
    • Conversations with Giants in Medicine
  • Reviews
    • View all reviews ...
    • Emerging therapeutic strategies in breast cancer (Oct 2026)
    • The cGAS-STING pathway: DNA sensing in health and disease (Jun 2026)
    • Neurodegeneration (Mar 2026)
    • Clinical innovation and scientific progress in GLP-1 medicine (Nov 2025)
    • Pancreatic Cancer (Jul 2025)
    • Complement Biology and Therapeutics (May 2025)
    • Evolving insights into MASLD and MASH pathogenesis and treatment (Apr 2025)
    • View all review series ...
  • Viewpoint
  • Collections
    • In-Press Preview
    • Clinical Research and Public Health
    • Research Letters
    • Letters to the Editor
    • Editorials
    • Commentaries
    • Editor's notes
    • Reviews
    • Viewpoints
    • 100th anniversary
    • Top read articles

  • Current issue
  • Past issues
  • Specialties
  • Reviews
  • Review series
  • ASCI Milestone Awards
  • Video Abstracts
  • Conversations with Giants in Medicine
  • In-Press Preview
  • Clinical Research and Public Health
  • Research Letters
  • Letters to the Editor
  • Editorials
  • Commentaries
  • Editor's notes
  • Reviews
  • Viewpoints
  • 100th anniversary
  • Top read articles
  • About
  • Editors
  • Consulting Editors
  • For authors
  • Journal stats
  • Publication ethics
  • Publication alerts by email
  • Advertising
  • Job board
  • Contact
Top
  • View PDF
  • Download citation information
  • Send a comment
  • Terms of use
  • Standard abbreviations
  • Need help? Email the journal
  • Top
  • Abstract
  • Rheumatoid factors in rheumatoid arthritis and beyond
  • Distinct genetic signatures
  • Distinct immune signatures
  • Implications and future directions
  • Conflict of interest
  • Funding support
  • Footnotes
  • References
  • Version history
  • Article usage
  • Citations to this article

Advertisement

Commentary Open Access | 10.1172/JCI210542

Why a positive rheumatoid factor test does not always mean rheumatoid arthritis

Luc Van Kaer1,2

1Department of Pathology, Microbiology and Immunology, Vanderbilt University Medical Center, Nashville, Tennessee, USA.

2Vanderbilt Institute for Infection, Immunology, and Inflammation, Vanderbilt University Medical Center, Nashville, Tennessee, USA.

Address correspondence to: Luc Van Kaer, Department of Pathology, Microbiology and Immunology, Vanderbilt University Medical Center, Room C-2217A, Medical Center North, 1161 21st Avenue South, Nashville, TN 37232, USA; Tel: 1-615.343.2707; Email: luc.van.kaer@vumc.org.

Find articles by Van Kaer, L. in: PubMed | Google Scholar |

Published October 1, 2026 - More info

Published in Volume 136, Issue 19 on October 1, 2026
J Clin Invest. 2026;136(19):e210542. https://doi.org/10.1172/JCI210542.
© 2026 Van Kaer et al. This work is licensed under the Creative Commons Attribution 4.0 International License. To view a copy of this license, visit http://creativecommons.org/licenses/by/4.0/.
Published October 1, 2026 - Version history
View PDF

Related article:

Rheumatoid factor production is genetically and molecularly distinct from rheumatoid arthritis
Mehmet Hocaoğlu, Amr H. Sawalha
Rheumatoid factor has unique genetic and immune features, separate from rheumatoid arthritis, helping explain why most carriers remain healthy
Clinical Research and Public Health Autoimmunity Genetics

Rheumatoid factor production is genetically and molecularly distinct from rheumatoid arthritis

  • Text
  • PDF
Abstract

BACKGROUND Rheumatoid factor (RF) autoantibodies are highly prevalent, yet the molecular determinants of RF development and its progression to rheumatoid arthritis (RA) remain poorly understood. Here, we define the genetic, phenotypic, and molecular architecture of RF and its progression to RA.METHODS A total of 469,036 UK Biobank participants with RF testing and 76 Allen Institute for Immunology–University of California, San Diego–University of Colorado Transition to Rheumatoid Arthritis (ALTRA) cohort individuals were studied. Phenome-wide association studies (PheWAS), GWAS, and proteome-wide association studies (PWAS) compared RF+ individuals who did not have autoimmune disease with RF– control individuals. Single-cell RNA-seq enabled pseudobulk differential expression and cytokine signature enrichment analyses.RESULTS RF seroprevalence was 9.3% and longitudinally stable in 94.5% of individuals. PheWAS identified 48 significant associations, led by chronic viral hepatitis (OR 4.8), hypersensitivity pneumonitis (OR 3.6), bronchiectasis (OR 1.9), and COPD (OR 1.4). GWAS of 24,216 RF+ individuals revealed 29 independent loci; the strongest signal was in the extended HLA region (OR 1.45, P = 5.4 × 10–221). Non-HLA loci converged on B cell homeostasis genes (ETS1, BACH2, PAX5, TNFRSF13B, FCGR2A). RF+ individuals did not carry elevated RA polygenic risk. Proteomics profiling identified 153 differentially abundant proteins enriched for humoral immunity and IFN-induced chemokines, with 79% showing dose response relationships across titers. Progression to RA involved a shift toward activating tissue-damaging inflammatory pathways rather than amplification of the RF signature. Single-cell transcriptomics of RF+ individuals without RA localized dysregulation to memory B cells, with downregulation of inhibitory genes (FCGR2B, BACH2, FOXP1) and upregulation of activation markers.CONCLUSION RF production is governed by HLA class II and B cell regulatory loci, associated with mucosal inflammation, and genetically and molecularly distinct from RA.FUNDING This study was supported by the Rheumatoid Arthritis Research Program Grant from the Arthritis Foundation.

Authors

Mehmet Hocaoğlu, Amr H. Sawalha

×

Abstract

Rheumatoid factors (RFs) are autoantibodies directed against the tail region of IgG antibodies and are present in a majority of people with rheumatoid arthritis (RA). RF production is commonly assessed to help diagnose RA, but its performance is limited due to low specificity and sensitivity for reasons that have remained unclear. In this issue of the JCI, Hocaoğlu and Sawalha shed light on this matter using extensive phenome-, genome-, transcriptome-, and proteome-wide association analyses of RF-seropositive and -seronegative individuals. They report that RF production was controlled by a genetic signature that included HLA and non-HLA genes and an immune signature reflective of B cell dysregulation but distinct from the genetic and immune signatures associated with RA. These findings explain the limited diagnostic value of RF testing in RA and may help refine the clinical management of RA and development of interventions that prevent or delay disease.

Rheumatoid factors in rheumatoid arthritis and beyond

Rheumatoid arthritis (RA), which affects 0.5%–1% of the population, is a systemic autoimmune disease that arises in genetically susceptible individuals as a result of environmental factors such as tobacco smoking and certain infections (1–3). Its pathology is characterized by infiltrating inflammatory cells and autoantibodies that mediate persistent inflammation of the joints. Among the hallmark autoantibodies of RA are rheumatoid factors (RFs), which are directed against the fragment crystallizable (Fc) region, that is, the tail end of IgG antibodies (4–7) (Figure 1). Most RFs have the IgM antibody isotype, but they can also exist as IgG and IgA isotypes. These antibodies were first discovered in 1937 (8) and coined RFs because of their association with RA in 1952, and RF serological status was introduced into the classification criteria for RA in 1958. Although RFs continue to serve as serological markers for the diagnosis of RA (9), their clinical value is limited due to low specificity and sensitivity (7, 10, 11).
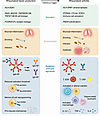
Genetic, environmental, and immune factors associated with asymptomatic RFFigure 1

Genetic, environmental, and immune factors associated with asymptomatic RF production compared with RA. Hocaoğlu and Sawalha (13) compared the genetic and systemic immune signatures of RF production in asymptomatic individuals (left) with the established genetic and peripheral immune signatures of patients with RA (right). In addition to differences in the genetic loci associated with either group, the study determined that RF production in genetically susceptible individuals may be associated with environmental factors such as smoking and certain infections that mediate mucosal inflammation. Over time, RF levels may rise and include non-IgM isotypes. In individuals who are also genetically susceptible to RA development, environmental factors such as infections may trigger progression toward RA and rapid induction of the systemic RA immune signature, which commonly includes production of ACPAs.

RFs are found in 60%–80% of patients with RA (4–7). They are thought to contribute to RA clinical disease activity by forming immune complexes that are deposited in the joint lining, resulting in complement system activation, macrophage recruitment, engulfment and destruction of the immune complexes, and production of proinflammatory mediators that instigate tissue damage. In patients with RA, high RF levels in the serum are associated with a poor prognosis and the development of extra-articular manifestations, i.e., damage to organ systems beyond the joints such as the heart and lungs (7), particularly when RFs of the IgA isotype are present, as these are associated with pulmonary lesions.

RFs are not unique to RA, as they can be elevated in a wide range of other conditions (4–7), including other autoimmune diseases (e.g., Sjögren’s syndrome and systemic lupus erythematosus), certain infections (e.g., hepatitis C and EBV infection and bacterial endocarditis), and conditions associated with mucosal inflammation (e.g., periodontal and pulmonary disease). RFs are also found in 3%–10% of healthy individuals, and prevalence increases with age, reaching up to 20%–25% in the elderly population (12). Positive serology for RFs in healthy individuals has limited predictive value for future RA development, unless high titers enriched for non-IgM isotypes are present (7).

Considering these limitations in the diagnostic and prognostic performance of RFs as biomarkers for RA, Hocaoğlu and Sawalha (13) asked whether the genetic and immune signatures associated with RF production mirror those previously identified for RA. Thus, these investigators interrogated large databases containing clinical, biomarker, genetic, and transcriptomic and/or proteomic information from RF-seropositive and -seronegative individuals to profile the genetic and immune landscapes associated with RF serostatus in the context of normal health, RA, and other conditions.
Distinct genetic signatures

The heritability of RA has been estimated at about 60%, accounting for over half of RA disease susceptibility in the general population (14). The most prominent genetic risk factor is located within the HLA class II region, specifically the HLA-DRB1 gene (15) (Figure 1). Distinct variants of this gene encode a shared epitope of 5 amino acids that forms a structural motif within the peptide-binding groove to facilitate the presentation of certain self-peptides to autoreactive, CD4-expressing T lymphocytes. In turn, these autoreactive helper T cells facilitate the development of autoantibodies directed against proteins or peptides modified by citrullination — a biological process whereby the amino acid arginine is converted into citrulline (16). Over 100 other non-HLA genetic loci have been implicated in RA susceptibility, including genes that control immune cell activity (e.g., protein tyrosine phosphatase nonreceptor type 22 [PTPN22], cytotoxic T lymphocyte antigen 4 [CTLA4], and STAT4) and protein citrullination (e.g., peptidyl arginine deiminase 4 [PADI4]) (1, 3).

Similar to RA, RF production has a strong genetic component. Earlier studies provided evidence that RA and RF production are controlled by distinct genetic loci (17). Hocaoğlu and Sawalha (13) similarly found a strong genetic association with RF-seropositive status. They discovered two susceptibility loci within the extended HLA region, including a locus strongly linked to the HLA-DQA1 gene. They also found less prominent associations with a variety of non-HLA genes, including genes affecting B cell identity, activation, differentiation, and survival (e.g., paired box 5 [PAX5], BTB and CNC homolog 2 [BACH2], TNF receptor superfamily member 8 [TNFRSF8], and TNF superfamily member 13B [TNFRSF13B]), as well as genes influencing Fc receptor biology (e.g., Fc γ receptor 2A [FCGR2A]) (Figure 1). Importantly, in sharp contrast to RF-seropositive patients with RA, the asymptomatic RF-seropositive population studied by Hocaoğlu and Sawalha (13) lacked a significant increase in RA genetic risk as compared with the seronegative control group. Thus, these findings provide strong evidence for distinct genetic risk factors associated with the production of RFs compared with RA.

Distinct immune signatures

The peripheral immune signature of RA reflects the systemic breakdown of immune tolerance mechanisms that unleash tissue-damaging inflammatory pathways. It is characterized by the generation of hallmark autoantibodies such as RFs and anti-citrullinated protein antibodies (ACPAs) (found in 70%–90% of patients with RA, and more specific to RA than RFs) (4, 5), macrophage activation, neutrophil degranulation, activation of naive B and T cells, expansion of effector T cells associated with inflammatory responses and B cell help, elevated inflammatory markers (e.g., erythrocyte sedimentation rate [ESR] and C-reactive protein [CRP]), and production of proinflammatory cytokines (e.g., IL-1β, IL-6, and TNF-α) (18) (Figure 1). These systemic immune alterations in RA were confirmed by Hocaoğlu and Sawalha (13). However, in individuals with asymptomatic RF production, they found a sharply distinct immune signature reflecting mild immune dysregulation, as noted by the induction of features of antibody production, immune complex regulation, IFN-mediated chemokine induction, antigen presentation, and reprogramming of the memory B cell compartment (Figure 1). Most notably, the memory B cells displayed an activated phenotype, and many expressed the death receptor CD95 (also known as FAS). Some of these alterations in the proteomic and transcriptional features of asymptomatic RF-seropositive individuals were consistent with the genetic risk factors for RF production that the investigators had identified.

Furthermore, the immune landscape of RF production Hocaoğlu and Sawalha uncovered was distinct from the peripheral immune phenotypes that previous studies observed in asymptomatic individuals producing ACPAs and in healthy first-degree relatives of patients with RA (19, 20). Interestingly, in asymptomatic RF-seropositive individuals who went on to develop RA, inflammatory and tissue-damaging pathways characteristic of RA appeared to arise at or near disease onset, suggesting that progression from asymptomatic RF production to RA is associated with a shift in immune signatures rather than gradual expansion of the RF signature. Collectively, these findings indicate that RF production and RA display distinct immune signatures and that progression of asymptomatic RF production to RA likely involves a rather quick transition from the mild B cell dysregulation signature of RF production to the more profound tissue-damaging signature of RA, perhaps triggered by environmental factors such as infection (Figure 1).

Implications and future directions

Hocaoğlu and Sawalha’s findings provide a molecular explanation for the limited value of RF testing in diagnosing RA (21). As RF production and RA are characterized by distinct genetic and immune signatures, the presence of RF antibodies is not directly linked to RA disease. Nevertheless, a gradual rise in RF serum levels, especially RFs with the IgG and IgA isotypes, often precedes the onset or diagnosis of RA (22). Hence, one way RF serology could help in predicting progression to RA would be to test RF-seropositive individuals for sequential elevations in RF isotypes — starting with IgM, and followed by IgG and IgA. Such individuals could then be tested for genetic susceptibility to RA and for the presence of ACPAs. Such testing might permit early intervention to alter the disease trajectory during the so-called “window of opportunity” in RA treatment (23). Similarly, since RFs have been implicated in the pathogenesis of RA, their status can inform disease prognosis, including the development of extra-articular manifestations (7). In this context, the phenome-wide association analyses performed by Hocaoğlu and Sawalha (13) confirmed an association between stable, asymptomatic RF production and respiratory diseases such as hypersensitivity pneumonitis, a finding consistent with the proposed mucosal origin of RF production and its progression to RA (24).

RF testing also holds promise for predicting the RA therapeutic response, as high RF titers have been associated with resistance to treatment with disease-modifying antirheumatic drugs, including conventional synthetic drugs such as methotrexate, and certain biological agents such as Fc receptor–containing anti–TNF-α antibodies that can be bound by RFs and targeted for degradation (25). Finally, the RF-associated immune signatures identified by Hocaoğlu and Sawalha (13) could be harnessed for therapeutic purposes. The molecular pathways associated with these immune signatures could serve as the foundation for developing precision therapeutics, utilizing existing drugs or novel compounds, in efforts to prevent or delay RF production and progression to RA or to modify the disease trajectory.

In conclusion, the study by Hocaoğlu and Sawalha (13) elegantly illustrates how multiomics data in clinical databases can be leveraged to better understand the genetic and molecular underpinnings of disease.

Conflict of interest

The author has declared that no conflict of interest exists.

Funding support

This work is the result of NIH funding, in whole or in part, and is subject to the NIH Public Access Policy. Through acceptance of this federal funding, the NIH has been given a right to make the work publicly available in PubMed Central. This work was supported in part by the following:

  • NIH grant R01AI139046 (to LVK).
Footnotes

Copyright: © 2026, Van Kaer et al. This is an open access article published under the terms of the Creative Commons Attribution 4.0 International License.

Reference information: J Clin Invest. 2026;136(19):e210542. https://doi.org/10.1172/JCI210542.

See the related article at Rheumatoid factor production is genetically and molecularly distinct from rheumatoid arthritis.

References
  1. Smolen JS, et al. Rheumatoid arthritis. Nat Rev Dis Primers. 2018;4:18001.
    View this article via: CrossRef PubMed Google Scholar
  2. Gravallese EM, Firestein GS. Rheumatoid arthritis - common origins, divergent mechanisms. N Engl J Med. 2023;388(6):529–542.
    View this article via: CrossRef PubMed Google Scholar
  3. Venetsanopoulou AI, et al. Epidemiology of rheumatoid arthritis: genetic and environmental influences. Expert Rev Clin Immunol. 2022;18(9):923–931.
    View this article via: CrossRef PubMed Google Scholar
  4. van Delft MAM, Huizinga TWJ. An overview of autoantibodies in rheumatoid arthritis. J Autoimmun. 2020;110:102392.
    View this article via: CrossRef PubMed Google Scholar
  5. Steiner G, Toes REM. Autoantibodies in rheumatoid arthritis - rheumatoid factor, anticitrullinated protein antibodies and beyond. Curr Opin Rheumatol. 2024;36(3):217–224.
    View this article via: CrossRef PubMed Google Scholar
  6. Tanaka Y. What is rheumatoid factor? From screening to personalized management. Rheumatology (Oxford). 2025;64(suppl_2):ii9–ii14.
    View this article via: CrossRef PubMed Google Scholar
  7. Togashi T, et al. Rheumatoid factor: diagnostic and prognostic performance and therapeutic implications in rheumatoid arthritis. J Clin Med. 2025;14(5):1529.
    View this article via: CrossRef PubMed Google Scholar
  8. Waaler E. On the occurrence of a factor in human serum activating the specific agglutination of sheep blood corpuscles. Acta Path Microbiol Scand. 1940;17(2):172.
    View this article via: CrossRef Google Scholar
  9. Aletaha D, et al. 2010 rheumatoid arthritis classification criteria: an American College of Rheumatology/European League Against Rheumatism collaborative initiative. Ann Rheum Dis. 2010;69(9):1580–1588.
    View this article via: CrossRef PubMed Google Scholar
  10. Motta F, et al. Rheumatoid factor isotypes in rheumatoid arthritis diagnosis and prognosis: a systematic review and meta-analysis. RMD Open. 2023;9(3):e002817.
    View this article via: CrossRef PubMed Google Scholar
  11. Szekanecz Z, et al. Diagnostic, prognostic and therapeutic biomarkers in rheumatoid arthritis. Nat Rev Rheumatol. 2026;22(8):496–513.
    View this article via: CrossRef PubMed Google Scholar
  12. Dillon CF, et al. Population-based estimates of humoral autoimmunity from the U.S. National Health and Nutrition Examination Surveys, 1960-2014. PLoS One. 2020;15(1):e0226516.
    View this article via: CrossRef PubMed Google Scholar
  13. Hocaoğlu M, Sawalha AH. Rheumatoid factor production is genetically and molecularly distinct from rheumatoid arthritis. J Clin Invest. 2026;136(19):e208390.
    View this article via: JCI PubMed CrossRef Google Scholar
  14. MacGregor AJ, et al. Characterizing the quantitative genetic contribution to rheumatoid arthritis using data from twins. Arthritis Rheum. 2000;43(1):30–37.
    View this article via: CrossRef PubMed Google Scholar
  15. Gregersen PK, et al. The shared epitope hypothesis. An approach to understanding the molecular genetics of susceptibility to rheumatoid arthritis. Arthritis Rheum. 1987;30(11):1205–1213.
    View this article via: CrossRef PubMed Google Scholar
  16. Vossenaar ER, et al. PAD, a growing family of citrullinating enzymes: genes, features and involvement in disease. Bioessays. 2003;25(11):1106–1118.
    View this article via: CrossRef PubMed Google Scholar
  17. Lawrence JS. Genetics of rheumatoid factor and rheumatoid arthritis. Clin Exp Immunol. 1967;2(suppl):769–783.
    View this article via: PubMed Google Scholar
  18. Weyand CM, Goronzy JJ. The immunology of rheumatoid arthritis. Nat Immunol. 2021;22(1):10–18.
    View this article via: CrossRef PubMed Google Scholar
  19. Inamo J, et al. Deep immunophenotyping reveals circulating activated lymphocytes in individuals at risk for rheumatoid arthritis. J Clin Invest. 2025;135(6):e185217.
    View this article via: JCI CrossRef PubMed Google Scholar
  20. He Z, et al. Progression to rheumatoid arthritis in at-risk individuals is defined by systemic inflammation and by T and B cell dysregulation. Sci Transl Med. 2025;17(817):eadt7214.
    View this article via: CrossRef PubMed Google Scholar
  21. Steiner G, et al. Classification of rheumatoid arthritis: is it time to revise the criteria? RMD Open. 2024;10(2):e003851.
    View this article via: CrossRef PubMed Google Scholar
  22. Nielen MM, et al. Specific autoantibodies precede the symptoms of rheumatoid arthritis: a study of serial measurements in blood donors. Arthritis Rheum. 2004;50(2):380–386.
    View this article via: CrossRef PubMed Google Scholar
  23. Mankia K, Emery P. A new window of opportunity in rheumatoid arthritis: targeting at-risk individuals. Curr Opin Rheumatol. 2016;28(3):260–266.
    View this article via: CrossRef PubMed Google Scholar
  24. Holers VM, et al. Rheumatoid arthritis and the mucosal origins hypothesis: protection turns to destruction. Nat Rev Rheumatol. 2018;14(9):542–557.
    View this article via: CrossRef PubMed Google Scholar
  25. Avci AB, et al. Rheumatoid factors revisited in the age of biologic therapy. Rheumatology (Oxford). 2025;64(suppl_2):ii15–ii24.
    View this article via: CrossRef PubMed Google Scholar
Version history
  • Version 1 (October 1, 2026): Electronic publication

Article tools

  • View PDF
  • Download citation information
  • Send a comment
  • Terms of use
  • Standard abbreviations
  • Need help? Email the journal

Metrics

  • Article usage
  • Citations to this article

Go to

  • Top
  • Abstract
  • Rheumatoid factors in rheumatoid arthritis and beyond
  • Distinct genetic signatures
  • Distinct immune signatures
  • Implications and future directions
  • Conflict of interest
  • Funding support
  • Footnotes
  • References
  • Version history
Advertisement
Advertisement

Copyright © 2026 American Society for Clinical Investigation
ISSN: 0021-9738 (print), 1558-8238 (online)

Sign up for email alerts